
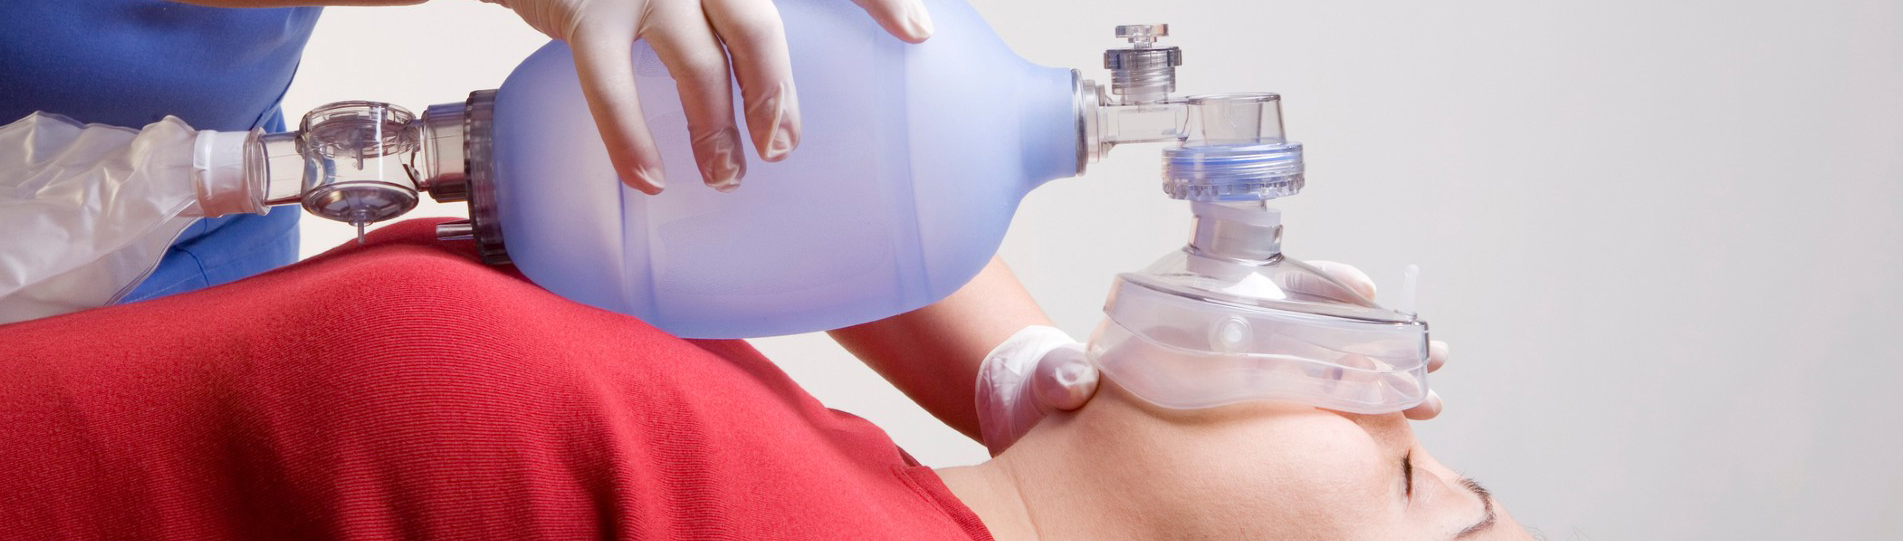

Immagina che un paziente collassi davanti a te. Smette di respirare. Sapresti cosa fare nei primi 60 secondi? La tua prima mossa: posizionare il paziente e liberare le vie aeree. Questa semplice azione fa risparmiare tempo prezioso.Maschera con valvola a sacco (BVM)Fornisce l'aria espirata necessaria per mantenere l'apporto di ossigeno.
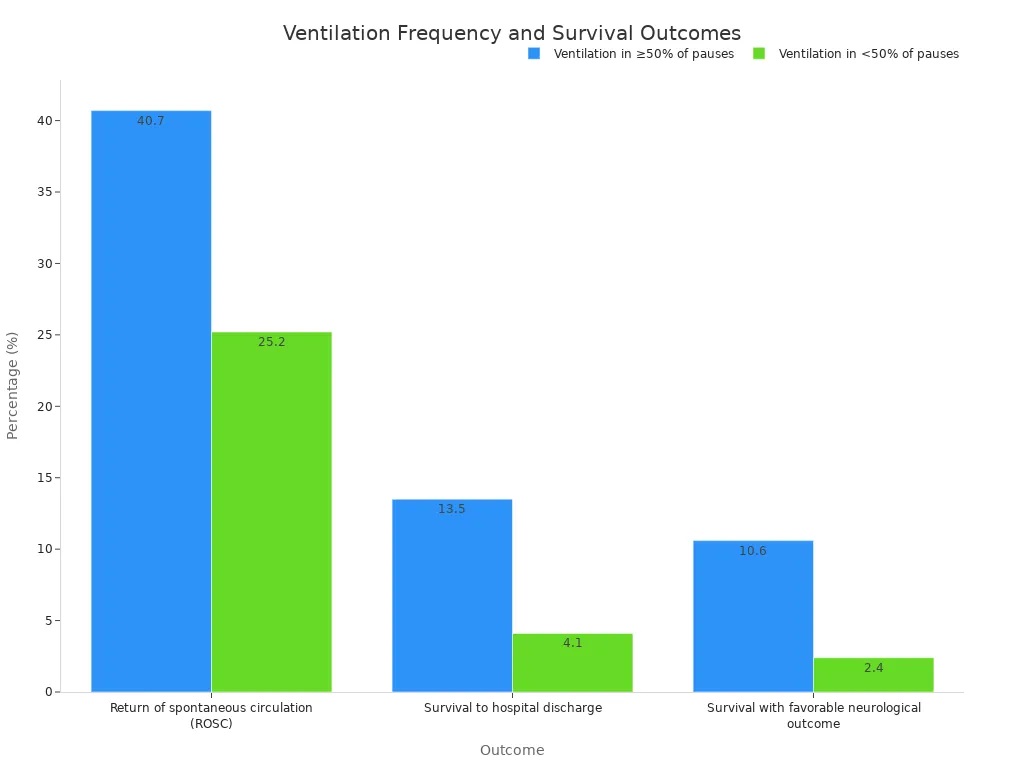
I dati provenienti da studi sull'arresto cardiaco dimostrano perché questo sia importante. I pazienti sottoposti a ventilazione durante almeno metà delle pause della rianimazione cardiopolmonare hanno raggiunto il 40,7% di ripristino della circolazione spontanea (ROSC) in ambito preospedaliero, contro il 25,2% di quelli con ventilazione meno frequente. La sopravvivenza alla dimissione è quasi triplicata.
Padroneggiare questa tecnica BVM è un'abilità fondamentale per l'assistenza di emergenza. I passaggi sono in linea con le linee guida standard di rianimazione. Attrezzature di qualità, come le maschere con valvola a sacco (BVM) diTianzuo Medical, garantisce una ventilazione efficace. Il tuo addestramento BLS getta le basi per questo. La certificazione BLS insegna questi principi fondamentali. Ogni soccorritore dovrebbe esercitarsi finché non diventino istintivi.
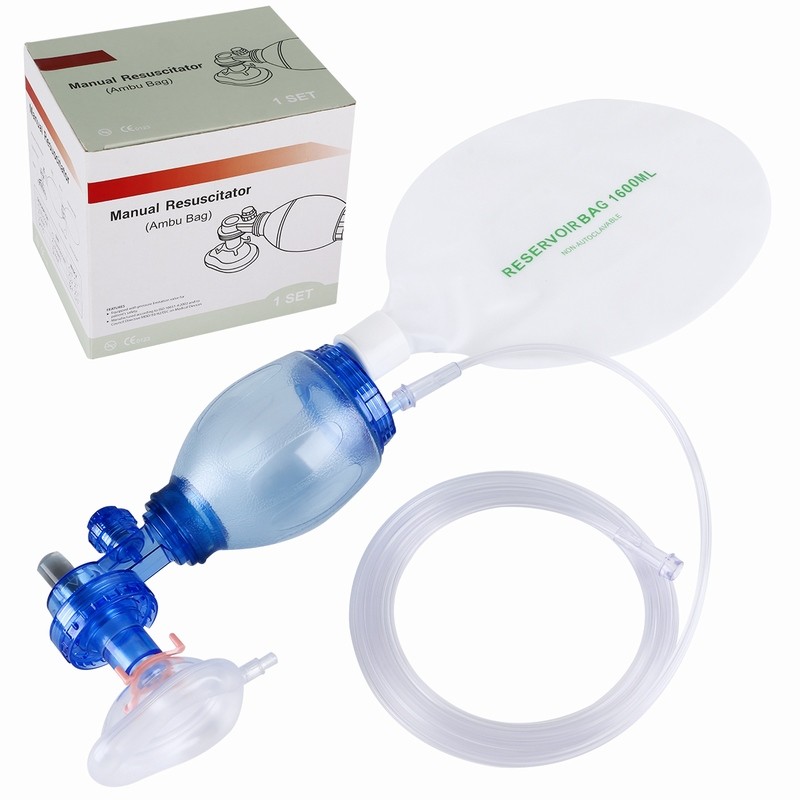
Una maschera con valvola a sacco è unarianimatore manualeQuesto dispositivo fornisce ventilazione a pressione positiva ai pazienti che non riescono a respirare autonomamente in modo adeguato. Premendo il sacchetto autoespandibile si immette aria o ossigeno nei polmoni del paziente, per poi rilasciarlo e consentire l'espirazione. Questo dispositivo funge da ponte tra la gestione di base delle vie aeree e gli interventi più complessi, permettendo di controllare ogni singolo respiro.
Comprendere ogni parte della maschera con valvola a sacco ti aiuta a usarla efficacemente durante un'emergenzaOgni componente svolge un ruolo specifico nel garantire una ventilazione sicura.
|
Componente |
Funzione |
|---|---|
|
Sacca di riserva di ossigeno |
Immagazzina ossigeno per garantire un'elevata erogazione di FiO2; si riempie quando l'ossigeno scarseggia.l'alimentazione è adeguata |
|
Ingresso ossigeno |
Si collega a una fonte di ossigeno per fornire ossigeno supplementare. |
|
Valvola di aspirazione (tre valvole a lembo) |
Controllo del flusso di gas: la membrana del disco di aspirazione impedisce il riflusso; la valvola a farfalla del serbatoio di ingresso consente l'aspirazione dell'aria ambiente quando l'apporto di ossigeno è insufficiente; la valvola a farfalla del serbatoio di uscita rilascia la pressione in eccesso per prevenire danni |
|
sacco di ventilazione |
Sacca autogonfiabile che viene compressa per consegnarer respira; si ritrae per riempirsi di ossigeno o aria |
|
Valvola paziente |
Dirige il flusso inspiratorio verso il paziente e il flusso espiratorio verso l'esterno per prevenire il rebreathing; include porte inspiratorie ed espiratorie. |
|
Valvola di sicurezza |
Previene la pressione eccessiva, soprattutto nei modelli pediatrici |
|
valvola PEEP |
Si collega alla porta espiratoria per mantenere una pressione positiva di fine espirazione. |
Il sacco di ventilazione si ritrae automaticamente dopo ogni compressione, aspirando gas fresco. Il sistema di valvole unidirezionali garantisce che l'aria espirata fuoriesca senza mescolarsi con l'ossigeno in entrata. Prima dell'uso, è necessario ispezionare ogni componente, in particolare le valvole, poiché una valvola bloccata può compromettere l'intero processo di ventilazione.
In diverse situazioni critiche, sarà necessario utilizzare un respiratore con maschera e pallone (BVM). L'insufficienza respiratoria è in cima alla lista: quando la respirazione del paziente è troppo superficiale o troppo debole per mantenere livelli di ossigeno adeguati. L'arresto cardiaco richiede una ventilazione BVM immediata durante la rianimazione cardiopolmonare (RCP), poiché le sole compressioni toraciche non sono sufficienti a fornire l'ossigeno necessario al cervello. Il dispositivo viene utilizzato anche per la preossigenazione prima dell'intubazione, riempiendo i polmoni del paziente con ossigeno ad alta concentrazione per creare un margine di sicurezza durante la procedura.
Il tuo addestramento BLS pone l'accento sul riconoscimento rapido di queste situazioni. La decisione di iniziare la ventilazione BVM dovrebbe essere presa entro pochi secondi dall'identificazione di una respirazione inadeguata. Ritardare questo intervento riduce le possibilità di sopravvivenza del paziente. In ogni caso, il tuo obiettivo rimane lo stesso: somministrare ossigeno in modo efficace preparandoti al contempo alla gestione definitiva delle vie aeree. Il pallone Ambu che tieni in mano rappresenta un anello critico nella catena della sopravvivenza e la gestione delle vie aeree inizia con il corretto posizionamento e la tenuta della maschera.
Prima di somministrare anche un solo respiro, è necessario preparare l'attrezzatura e il paziente. Questa fase della gestione delle vie aeree determina il successo o il fallimento della ventilazione con pallone autoespandibile (BVM). Una ventilazione BVM efficace richiede un'attenta preparazione.
Il primo passo è selezionare la taglia corretta della maschera. Le maschere per adulti, bambini e neonati differiscono per forma e volume. Una maschera che non aderisce bene crea spazi vuoti e perdite. Ispeziona ogni componente della maschera con valvola a sacco per verificare la presenza di danni visibili. Comprimi il sacco e osservalo mentre si ritrae completamente. Questo conferma l'integrità della maschera con valvola a sacco. Testa la valvola di sicurezza comprimendo il sacco e verificando che si apra e si chiuda correttamente. Ispeziona la maschera facciale per individuare crepe, strappi o imbottitura usurata che potrebbero causare perdite. Prestazioni costanti dipendono da un sistema a tenuta stagna.
Assemblare il pallone autoespandibile, la maschera della misura appropriata, il tubo dell'ossigeno e il serbatoio. Collegare l'erogazione di ossigeno e impostare la portata a 10-15 L/min. Fissare saldamente tutti i collegamenti. I tubi dell'ossigeno non fissati correttamente possono scollegarsi durante l'uso. Un'importante avvertenza per la conservazione: se un rianimatore con pallone autoespandibile e maschera (BVM) non è progettato per essere comprimibile, conservarlo compresso per lunghi periodi può ridurne l'elasticità. Ciò compromette l'efficacia in caso di emergenza. Le valvole di sicurezza, comuni nei modelli pediatrici, impediscono la sovrapressione dei polmoni. Una clip di bypass consente l'azionamento manuale quando è clinicamente necessaria una pressione maggiore. La formazione BLS dovrebbe includere l'ispezione di questi dettagli. Buone abitudini BLS consentono di risparmiare tempo durante le emergenze reali.
Posizionare il paziente supino su una superficie piana e stabile. Questa posizione consente di accedere alle vie aeree. Aprire le vie aeree utilizzando le tecniche di posizionamento appropriate. Per i pazienti non traumatizzati, utilizzare la manovra di inclinazione della testa e sollevamento del mento. Inclinare la testa all'indietro premendo sulla fronte. Sollevare il mento in avanti con la punta delle dita. Questa azione solleva la lingua dalla parte posteriore della gola.
Per i pazienti con sospetta lesione spinale, utilizzare invece la manovra di spinta mandibolare. Posizionare le dita dietro l'angolo della mandibola e sollevarla in avanti senza inclinare la testa. Entrambe le tecniche sfruttano le prominenze ossee per ottenere un vantaggio meccanico. Evitare di comprimere i tessuti molli sotto la lingua, poiché ciò potrebbe causare un'ostruzione.
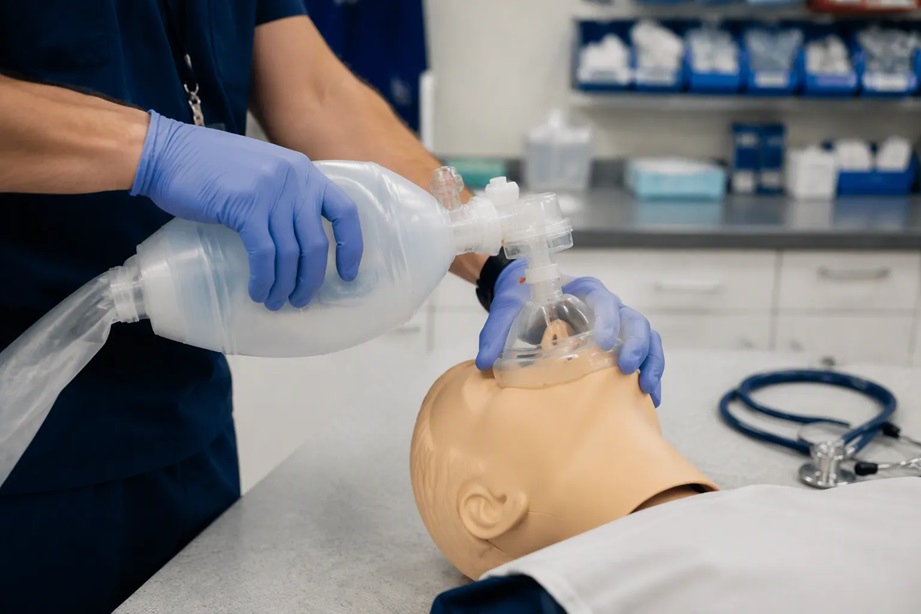
Posizionare correttamente la maschera. Posizionare l'estremità più stretta sul ponte del naso. La maschera deve coprire completamente sia il naso che la bocca, evitando qualsiasi spazio vuoto. Se il paziente è edentulo, lasciare la protesi dentaria in sede può migliorare la tenuta della maschera. Gli ausili nasofaringei e orofaringei aiutano a spingere in avanti la lingua e i tessuti molli. Questi sono particolarmente utili nei pazienti non responsivi. La tecnica deve includere la verifica dell'espansione toracica ad ogni respiro. Questo conferma l'efficacia della ventilazione con maschera a sacco (BVM). Le maschere a sacco (BVM) di produttori affidabili garantiscono prestazioni costanti.
Utilizzare un pallone autoespandibile da soli rappresenta una sfida significativa. È necessario gestire le vie aeree, sigillare la maschera e comprimere il pallone contemporaneamente. Padroneggiare questa tecnica da soli rimane una competenza fondamentale del BLS (Basic Life Support). Il successo dipende da due azioni critiche: ottenere una tenuta ermetica e somministrare la respirazione con un controllo preciso.
The foundation of effective bvm ventilation is a perfect mask seal. Without it, air escapes, and your efforts fail. The E-C clamp technique provides the mechanical advantage you need for one-handed control. Form a "C" with your thumb and index finger. Place these digits on the top of the mask, applying gentle downward pressure over the bridge of the nose and the bony part of the chin. Your remaining three fingers form an "E." Hook these fingers under the angle of the patient's jaw, along the bony ridge.
Your primary action is to lift the jaw upward into the mask. Do not push the mask down onto the face. Pushing the mask down often distorts the seal and can occlude the airway. Lifting the jaw pulls the tongue and soft tissues forward, opening the airway naturally. This lift creates the space for air to flow. Proper mask placement is confirmed when the mask covers the nose and mouth completely, with the cushion forming a seal against the skin.
Common errors during this process directly compromise ventilation. You must recognize and avoid them.
|
Error |
Impact on Ventilation |
|---|---|
|
Applying pressure to soft tissues of the neck |
Can occlude the airway, impairing ventilation. |
|
Pushing the mask down instead of lifting the jaw |
Can occlude the airway, reducing airflow. |
|
Squeezing the bag too hard or too fast |
Causes stomach insufflation, aspiration risk, and decreased cardiac output, compromising effective ventilation. |
Your goal is a stable, leak-free connection. A high-quality Bag Valve Mask (BVM) with a pliable, conforming cushion makes this seal easier to achieve and maintain.
With a secure seal established, you now focus on the breath itself. Your left hand maintains the E-C clamp. Your right hand squeezes the self-inflating bag. Compress the bag smoothly and deliberately. Aim to deliver each breath over a full second. Watch for the patient's chest to rise. This visible rise is your immediate feedback for adequate tidal volume.
You must control the volume and rate. Squeeze only one-third to one-half of the bag's total volume for an adult. A full compression forces too much air too quickly. This leads to gastric insufflation, where air enters the stomach. A distended stomach increases the risk of vomiting and aspiration. It also pushes against the diaphragm, reducing lung capacity. After each breath, allow the bag to recoil fully before delivering the next. Full recoil ensures the bag refills with oxygen.
Control your ventilation rate. For a patient with a pulse but absent breathing, provide one breath every 5 to 6 seconds. This equals 10 to 12 breaths per minute. During cardiac arrest with ongoing CPR, you will follow the 30:2 compression-to-ventilation ratio. In either case, a slow, measured pace is critical. Rapid, forceful bag squeezes are dangerous. They can decrease cardiac output by raising intrathoracic pressure, which impedes blood return to the heart.
The limitations of the one-person method are important to understand.
One-rescuer BVM ventilation with minimal training fails to deliver adequate tidal volumes, while two-rescuer BVM ventilation delivers tidal volumes more than recommended and comparable to those seen with endotracheal intubation. Therefore, two-rescuer BVM is more effective for initial resuscitation.
This evidence highlights a key point. The single-rescuer technique is physically demanding. Fatigue can quickly degrade your mask seal and the quality of your squeezes. Your bls training prepares you to use this method when you are alone. You should always call for help to transition to a two-person technique as soon as possible. ReliableBag-Valve-Mask (BVM) Resuscitatorssupport consistent performance, but your technique dictates the outcome. Focus on a good seal, watch for chest rise, and deliver slow, steady breaths to provide safe, effective positive-pressure ventilation.
When you integrate bvm ventilation into CPR, your timing matters. The goal is to deliver oxygen without interrupting blood flow. Data from a multicenter study shows the impact of effective ventilation. Patients who received lung inflation in at least half of the chest compression pauses achieved 40.7% return of spontaneous circulation. Those with less frequent ventilation reached only 25.2%. Survival to hospital discharge nearly tripled, from 4.1% to 13.5%.
Your technique during CPR follows a specific sequence. Deliver one bvm breath over one second. Watch for the chest to rise visibly. Provide only enough air to achieve this rise. Avoid over-ventilating, as excessive pressure increases intrathoracic pressure and reduces blood return to the heart. If an advanced airway is in place, you switch to continuous compressions. Give one breath every six seconds, at a ventilation rate of 10 breaths per minute, without synchronizing with compressions. A Bag-Valve-Mask (BVM) Resuscitator connected to high-flow oxygen supports this rhythm. Your bls training emphasizes minimizing interruptions in chest compressions. Every pause reduces perfusion to the brain and heart. Consistent chest movement and end-tidal CO₂ monitoring confirm effective ventilation.
The 30:2 compression-to-ventilation ratio is the standard for adult CPR. You perform 30 chest compressions, then pause briefly to deliver 2 breaths. This cycle repeats without delay. Evidence from ILCOR guidelines supports this ratio over alternatives like 15:2.
|
Outcome |
30:2 vs 15:2 Effect Estimate |
|---|---|
|
Favorable neurological function |
RR 1.34 (95% CI 1.02–1.76) |
|
Survival |
RR 1.37 (95% CI 1.19–1.59) |
|
Return of spontaneous circulation |
RR 1.11 (95% CI 1.00–1.23) |
The 30:2 ratio prioritizes chest compressions. By limiting pauses to 2 breaths, you maintain blood flow while still providing ventilation. Each breath should last one second. Squeeze only one-third to one-half of the bag volume. This prevents gastric insufflation and maintains cardiac output. During cardiac arrest, a two-person bvm technique is far more effective. One rescuer holds the mask seal while the other squeezes the bag. This reduces fatigue and delivers more consistent tidal volumes. Your bls certification should include practice with both single-rescuer and two-person techniques. Mastering this ratio during CPR ensures you balance ventilation with circulation, giving the patient the best chancefor survival.
When a second rescuer arrives, you should transition immediately to the two-person approach. This method transforms your bvm from a challenging solo task into a coordinated team effort. The two-rescuer technique dramatically improves the quality of bvm ventilation and represents the standard of care in resuscitation scenarios. Your bls training should emphasize this transition as a priority once help arrives.
The two-rescuer technique assigns distinct responsibilities to each team member. Rescuer 1, the Airway Manager, positions at the patient's head. This rescuer uses both hands to secure the mask with a double E-C clamp technique. Your thumbs and index fingers form a "C" shape on the mask surface. Your middle, ring, and little fingers form an "E" along the jawline to lift the mandible upward. You hold the mask stable on the face, lifting the jaw toward the mask rather than pressing the mask down. This action creates a reliable seal without compressing soft tissues. You must reassess the seal after every breath to maintain effectiveness.
Rescuer 2, the Bag Handler, manages the ventilation bag. This rescuer delivers slow, controlled squeezes and stops when visible chest rise occurs. You watch the patient's chest carefully for adequate rise and check for air leaks around the mask. You avoid forceful breaths that cause gastric inflation. Your body mechanics matter: maintain a comfortable position without twisting or reaching awkwardly.
|
Rescuer |
Specific Duties |
|---|---|
|
Rescuer 1 (Airway Manager) |
Positions at the patient's head;uses double E-C clamp; holds mask stable; lifts jaw toward mask; reassesses seal after each breath |
|
Rescuer 2 (Bag Handler) |
Delivers slow, controlled squeezes; stops at visible chest rise; watches for leaks; avoids forceful breaths; maintains proper body mechanics |
The two-rescuer technique offers clear advantages over the single-rescuer method. You achieve a better mask seal because one person dedicates both hands to airway management. This eliminates the struggle of maintaining the E-C clamp while simultaneously squeezing the bag. The result is more consistent tidal volumes with each breath.
Rescuer fatigue decreases significantly. In the one-person method, your hands tire quickly, degrading the seal quality. With two rescuers, each person focuses on one task, sustaining high performance for longer periods. This matters during prolonged resuscitation efforts where quality degrades over time.
Coordination between rescuers follows a specific sequence:
Rescuer 1 performs 30 chest compressions, counting aloud to maintain rhythm.
Rescuer 2, positioned at the head, holds the bag-mask with a C-shaped grip using thumb and index finger to seal the mask, while remaining fingers lift the jaw to open the airway.
Rescuer 2 administers two breaths, each lasting one second, while observing chest rise.
Rescuers switch duties every two minutes, with the rescuer performing compressions calling out "switch."
Counting out loud helps both rescuers anticipate breaths and maintain the correct compression-to-ventilation ratio. This verbal coordination prevents missed breaths or delayed compressions. Your bls training should include practice with this switching protocol to build muscle memory.
The two-rescuer technique also reduces the risk of over-ventilation. With one person dedicated to watching chest rise, you can stop each squeeze precisely when the chest reaches full expansion. This prevents the gastric insufflation and decreased cardiac output associated with excessive pressure. Bag-Valve-Mask (BVM) Resuscitators with clear markings help the Bag Handler gauge appropriate squeeze volumes.
Evidence supports this approach strongly. One-rescuer bvm ventilation with minimal training fails to deliver adequate tidal volumes. Two-rescuer bvm ventilation delivers tidal volumes more than recommended and comparable to those seen with endotracheal intubation. Therefore, two-rescuer bvm ventilation is more effective for initial resuscitation. When a second rescuer is available, this method is always the recommended approach. Your Bag Valve Masks (BVM) equipment performs best when paired with proper two-person technique. Master this coordination through regular practice, and you will provide safer, more effective ventilation during critical emergencies.
You must confirm your bvm delivery is working. The most reliable indicator remains visible chest rise and fall. As one clinical educator warns, "If you do not see the patient's chest rise and fall, your seal is not tight or the airway is not open, and the patient is not receiving the life-saving oxygen they need." Monitor oxygen saturation. A rising SpO₂ reading confirms effective ventilation. Watch for heart rate normalization. In bradycardic patients, an improving heart rate signals adequate oxygenation. Check for improved skin color as circulation returns. Your bls training teaches you to reassess these signs of effective ventilation continuously. Do not assume your technique is correct without verifying these indicators.
Even trained professionals make mistakes. A study by Culbreth and Gardenhire (2021) inHeart & Lungfound that respiratory therapists frequently fail to meet recommended ventilation parameters, including tidal volume and rate. Underventilation often results from a poor mask seal. Overventilation occurs when you squeeze too hard or too fast. Both errors reduce the effectiveness of your bvm ventilation.
|
Pitfall |
Corrective Action |
|---|---|
|
Over-ventilation |
Deliver each breath overone second. Squeeze only one-third to one-half of the bag volume. |
|
Poor mask seal |
Use the E-C clamp technique. Lift the jaw into the mask. Grasp bone, not soft tissue. |
|
Incorrect head positioning |
Reapply the head tilt-chin lift or jaw thrust maneuver to open the airway. |
|
Failure to monitor |
Check chest rise, SpO₂, and heart rate after every breath cycle. |
Over-ventilation raises intrathoracic pressure and decreases cardiac output. Control your driving pressure. Use a gentle squeeze over the full one-second inspiratory time. Allow complete exhalation by following the three-second rule. This prevents gas trapping and maintains proper ventilation.
Poor mask seal is the most common cause of underventilation. If you grasp the soft tissue beneath the mandible, you push the tongue into the posterior pharynx and worsen obstruction. Pull the mandible into the mask rather than pushing the mask onto the face.
Optimize airflow with airway adjuncts. An oral or nasal airway creates a consistent pathway that promotes laminar flow and reduces turbulence. If ventilation remains inadequate, the tongue may be obstructing the airway. Insert an adjunct to displace the tongue forward.
Monitor bag compliance. If the bag feels stiff, lung compliance is low. If pressure builds quickly, resistance is high. Adapt your technique accordingly. For high-resistance conditions like asthma, extend exhalation times. For low-compliance conditions like CHF, consider applying PEEP. Your bag valve mask technique must adapt to the patient's physiology.
Your bls training provides the foundation. Regular practice on mannequins builds muscle memory. Reliable Bag-Valve-Mask (BVM) Resuscitators support consistent performance, but your technique determines the outcome.
Mastering the bag valve mask requires more than reading. You must practice each step until it becomes instinct. Prepare your equipment. Position the patient. Seal the mask with the E-C clamp technique. Ventilate slowly and monitor the chest rise. A good seal forms the foundation of effective bvm ventilation. Over-ventilation causes harm. Remember the goal: slow and steady breaths. Your ambu bag skills need regular practice on mannequins. This builds muscle memory for real emergencies. Enroll in bls or ACLS training. These courses provide hands-on training with professional instructors. Keep your ambu device ready for immediate use. Reliable equipment like Bag-Valve-Mask (BVM) Resuscitators supports your cpr efforts. Your bls certification prepares you for this critical intervention.
Watch the patient's chest. Each breath should take one full second. If you deliver more than 10-12 breaths per minute for a patient with a pulse, you're going too fast. Rapid ventilation causes stomach inflation and reduces blood flow to the heart.
Stop ventilation immediately. Turn the patient's head to the side. Clear the airway with suction or a finger sweep. Reposition the head and resume bvm ventilation. Check that the mask seal remains intact before continuing. This prevents aspiration into the lungs.
No. Pediatric patients require smaller mask sizes and lower bag volumes. Use a pediatric-specific Bag-Valve-Mask (BVM) Resuscitator with a pressure relief valve. Deliver breaths gently, watching for subtle chest rise. Over-ventilation harms children faster than adults due to their smaller lung capacity.
Assign one rescuer to hold the mask seal during transport. That person focuses only on maintaining the E-C clamp position. Another rescuer squeezes the bag. This division of roles keeps the seal stable while the stretcher moves. Practice this coordination during your bls training.
Una maschera tascabile utilizza l'aria espirata, fornendo circa il 16% di ossigeno. Una maschera con pallone autoespandibile (BVM) si collega a una fonte di ossigeno, fornendo fino al 100% di ossigeno. Le maschere con pallone autoespandibile (BVM) offrono inoltre un migliore controllo del volume corrente e riducono l'affaticamento del soccorritore durante le manovre di rianimazione prolungate.

 Rete IPv6 supportata


 italiano
 English
 فارسی
 français
 Deutsch
 русский
 español
 português
 العربية
 Türkçe

